
What Men Keep Getting Wrong About Urological Cancer Screening
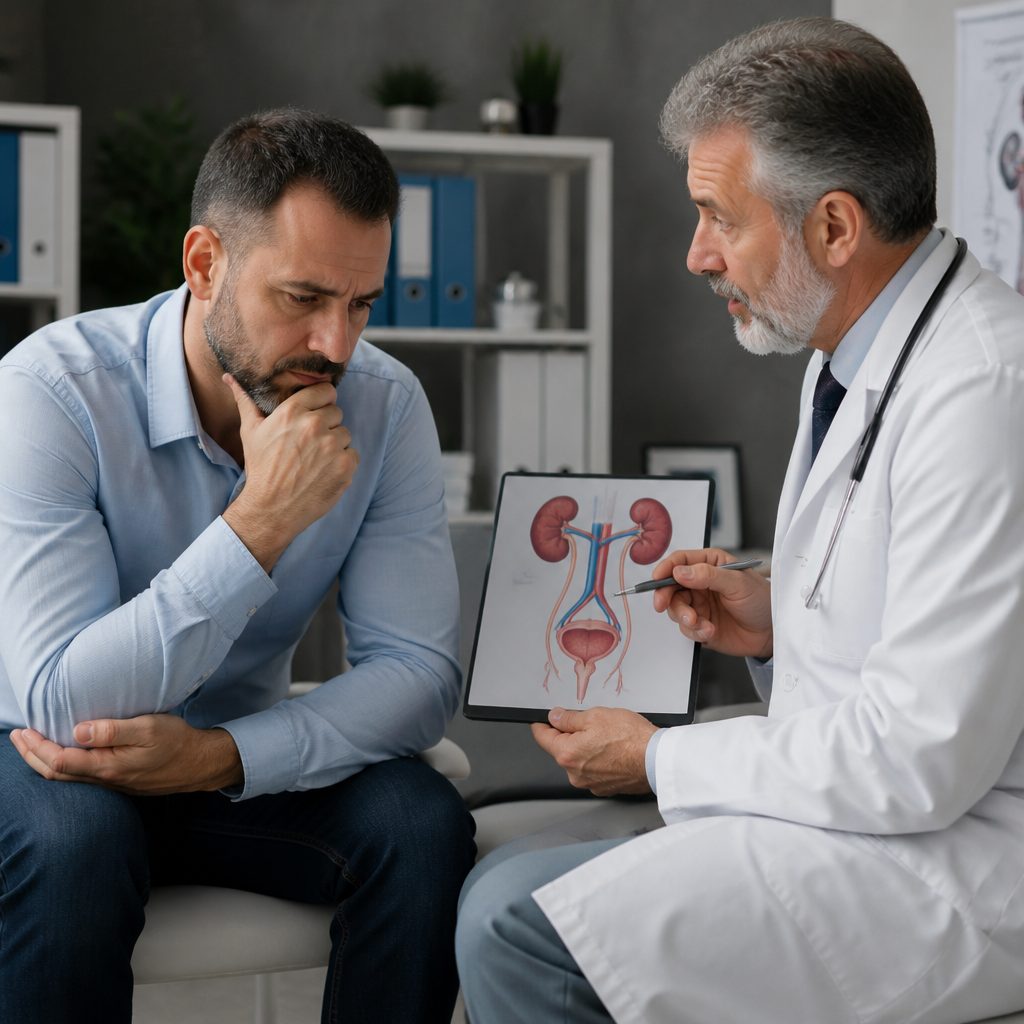
Most men don’t avoid the urologist because they’re uninformed. They avoid it because the appointment feels like an admission that something might be wrong — and because nobody has ever explained what actually happens in the room. Meanwhile, the three cancers that most commonly affect the male urinary and reproductive tract — testicular, prostate and bladder — all share one unglamorous trait: they are far easier to manage when found early, and far harder when found late.
This is a practical guide to what each of those cancers looks like, who should be paying attention at what age, and how to tell a real symptom from background noise.
Testicular cancer: the young man’s cancer nobody warns you about
Testicular cancer is unusual among cancers because it skews young — it is most often diagnosed in men roughly between their late teens and late thirties. That demographic is also the least likely to have a regular doctor, the least likely to mention a lump to anyone, and the most likely to assume a swelling is a sports injury that will settle down.
The signs are usually physical and findable:
- A firm, painless lump or hardened area on one testicle
- A change in size, shape or heaviness on one side
- A dull ache in the groin or lower abdomen
- Fluid collecting in the scrotum, or an unfamiliar pressure sensation
A monthly self-check in a warm shower takes about a minute. Roll each testicle between thumb and fingers; the soft tube running along the back is the epididymis and it belongs there. What you’re watching for is asymmetry that is new, and firmness where there was none. Risk goes up with a personal history of an undescended testicle, a previous tumor in the other testicle, or a family history. Evaluation is typically straightforward — a physical exam, a scrotal ultrasound and blood tests for tumor markers.
Prostate cancer: the one where the conversation matters more than the test
Prostate cancer is common and frequently slow-moving, which is exactly what makes it confusing. Many men live for decades with disease that never threatens them; others have aggressive tumors that need treating promptly. Screening exists to tell those two groups apart, not to find cancer in everyone.
The usual starting point is a PSA blood test, often alongside a digital rectal exam. PSA is a signal, not a verdict — levels rise with age, benign enlargement, infection, recent cycling and even recent ejaculation. That is why a single number rarely drives a decision. What clinicians look at is the trend over time, the result in the context of prostate size and age, and whether imaging such as multiparametric MRI shows a lesion worth sampling before any biopsy is considered.
When to start asking
Most guidance points to a first discussion around age 50 for men at average risk, and earlier — often around 40 to 45 — for men with a father or brother diagnosed young, men of African ancestry, or those with known inherited risk such as BRCA mutations. Symptoms worth raising include weak or interrupted urine flow, waking repeatedly at night to urinate, difficulty starting, blood in urine or semen, and new pelvic or lower back pain. Many of these are caused by benign prostatic enlargement rather than cancer, but they still deserve assessment.
Treatment is a set of trade-offs, not a single answer
For low-risk disease, active surveillance — structured monitoring with repeat PSA, imaging and biopsies — spares men the side effects of treatment they may never need. For disease that requires intervention, options include surgery, radiation oncology approaches including stereotactic radiotherapy, focal treatments such as high-intensity focused ultrasound in selected cases, and systemic therapy for advanced disease. Each carries a different profile of risk to urinary control and sexual function, and the right choice depends on tumor grade, stage, age and what the individual man is willing to live with.
Bladder and urothelial cancer: one symptom you should never rationalize
Painless blood in the urine is the symptom that gets explained away most often — attributed to dehydration, a hard gym session, or something eaten. Sometimes it is visible and pink; sometimes it is found only on a urine test. Either way, visible blood in the urine in an adult warrants investigation, even if it happens once and never returns.
Smoking is the dominant modifiable risk factor for bladder cancer, with occupational exposure to certain industrial chemicals, dyes and solvents also contributing. Chronic irritation and frequent urinary infections play a role in some cases. Work-up usually combines urine testing, imaging of the upper urinary tract, and cystoscopy — a thin camera passed into the bladder, which sounds worse than most patients report it being. Many bladder tumors are non-muscle-invasive at diagnosis and are managed with resection plus treatments placed directly into the bladder, followed by surveillance; muscle-invasive disease calls for more extensive surgery, chemotherapy or radiation.
Where specialist care changes the plan
The practical difference between a good outcome and a complicated one is often the quality of the staging and the breadth of the team reviewing it. A man with a raised PSA wants imaging and pathology read by people who look at genitourinary cases all day, and a treatment plan that has been argued over by surgeons, medical oncologists and radiation oncologists rather than decided in isolation. In Abu Dhabi, patients from across the UAE and abroad are seen through the Cancer Institute at Cleveland Clinic Abu Dhabi, where the urological cancer programs cover testicular, prostate and bladder or urothelial disease; a man seeking a Prostate cancer doctor there is evaluated with PSA testing and dedicated cancer imaging and pathology input, with cases reviewed by a multidisciplinary Tumor Board and the option of treatments including HIFU and stereotactic or Ethos adaptive radiotherapy, in collaboration with Cleveland Clinic in the US.
The part of diagnosis that isn’t medical
The weeks between a suspicious test and a confirmed plan are the hardest, and men often handle them badly — by going silent, overworking, or reading everything and sleeping through none of it. Building the kind of mental strength that holds up under uncertainty is genuinely part of the treatment path: sleeping on a schedule, keeping exercise going, telling at least two people the truth, and writing questions down before appointments so the visit isn’t wasted on things you’ll forget to ask.
It also helps to understand that staged, multidisciplinary cancer care follows similar logic across tumor types. Reading how diagnosis and treatment decisions are sequenced in a plain-language overview of breast cancer diagnosis and treatment makes the vocabulary — grade, stage, margins, adjuvant therapy, surveillance — far less intimidating when it’s your own scan being discussed.
A short list worth acting on
- Under 40: check your testicles monthly and get any new firm lump looked at within days, not months.
- Around 45 to 50: have a real conversation about PSA testing, earlier if cancer runs in your family.
- Any age: visible blood in the urine means book an appointment, even once.
- If you smoke, quitting is the single biggest thing you can do for your bladder.
- Ask for your numbers in writing. Trends matter more than snapshots, and you want a record.
None of this requires courage so much as scheduling. The men who do well are rarely the ones with no symptoms — they’re the ones who treated an odd symptom as information rather than a threat, and made the call early.